

Muscle recovery is where peptide claims often outrun the human evidence. Peptides for muscle tissue research are short amino-acid chains studied for their ability to signal biological pathways involved in muscle growth, repair, and inflammation. Large-scale human clinical trials and reputable data supporting claims that peptides enhance muscle growth or recovery are lacking.
It’s reasonable to ask whether peptides for muscle tissue research can affect muscle biology. The body naturally produces peptides that act as signals, and research examines how different peptides interact with tissue and cellular pathways. But biological activity, findings from laboratory or animal studies, and demonstrated benefits in people are not interchangeable.
This article explains how peptides act in the body, what muscle-growth and recovery studies suggest, and where the evidence remains limited. It also covers potential side effects, long-term safety concerns, and why research-grade materials should not be confused with products approved for human use.
Key Takeaways
- Separate findings from laboratory and animal studies from evidence in people when assessing claims about muscle growth or recovery.
- A meta-analysis of 19 studies found statistically significant effects favoring collagen peptide supplementation for fat-free mass, but that finding doesn’t establish benefits for every peptide or use.
- Understand that peptides are short amino-acid chains, and their effects depend on how they interact with biological signaling pathways.
- Consider reported effects such as nausea, headache, fatigue, and injection-site irritation alongside concerns about contamination and uncertain long-term safety.
- Explore tissue repair and recovery research through EuroLab Peptides when research-grade materials are relevant to your scientific inquiry.
What are the best peptides for muscle growth?
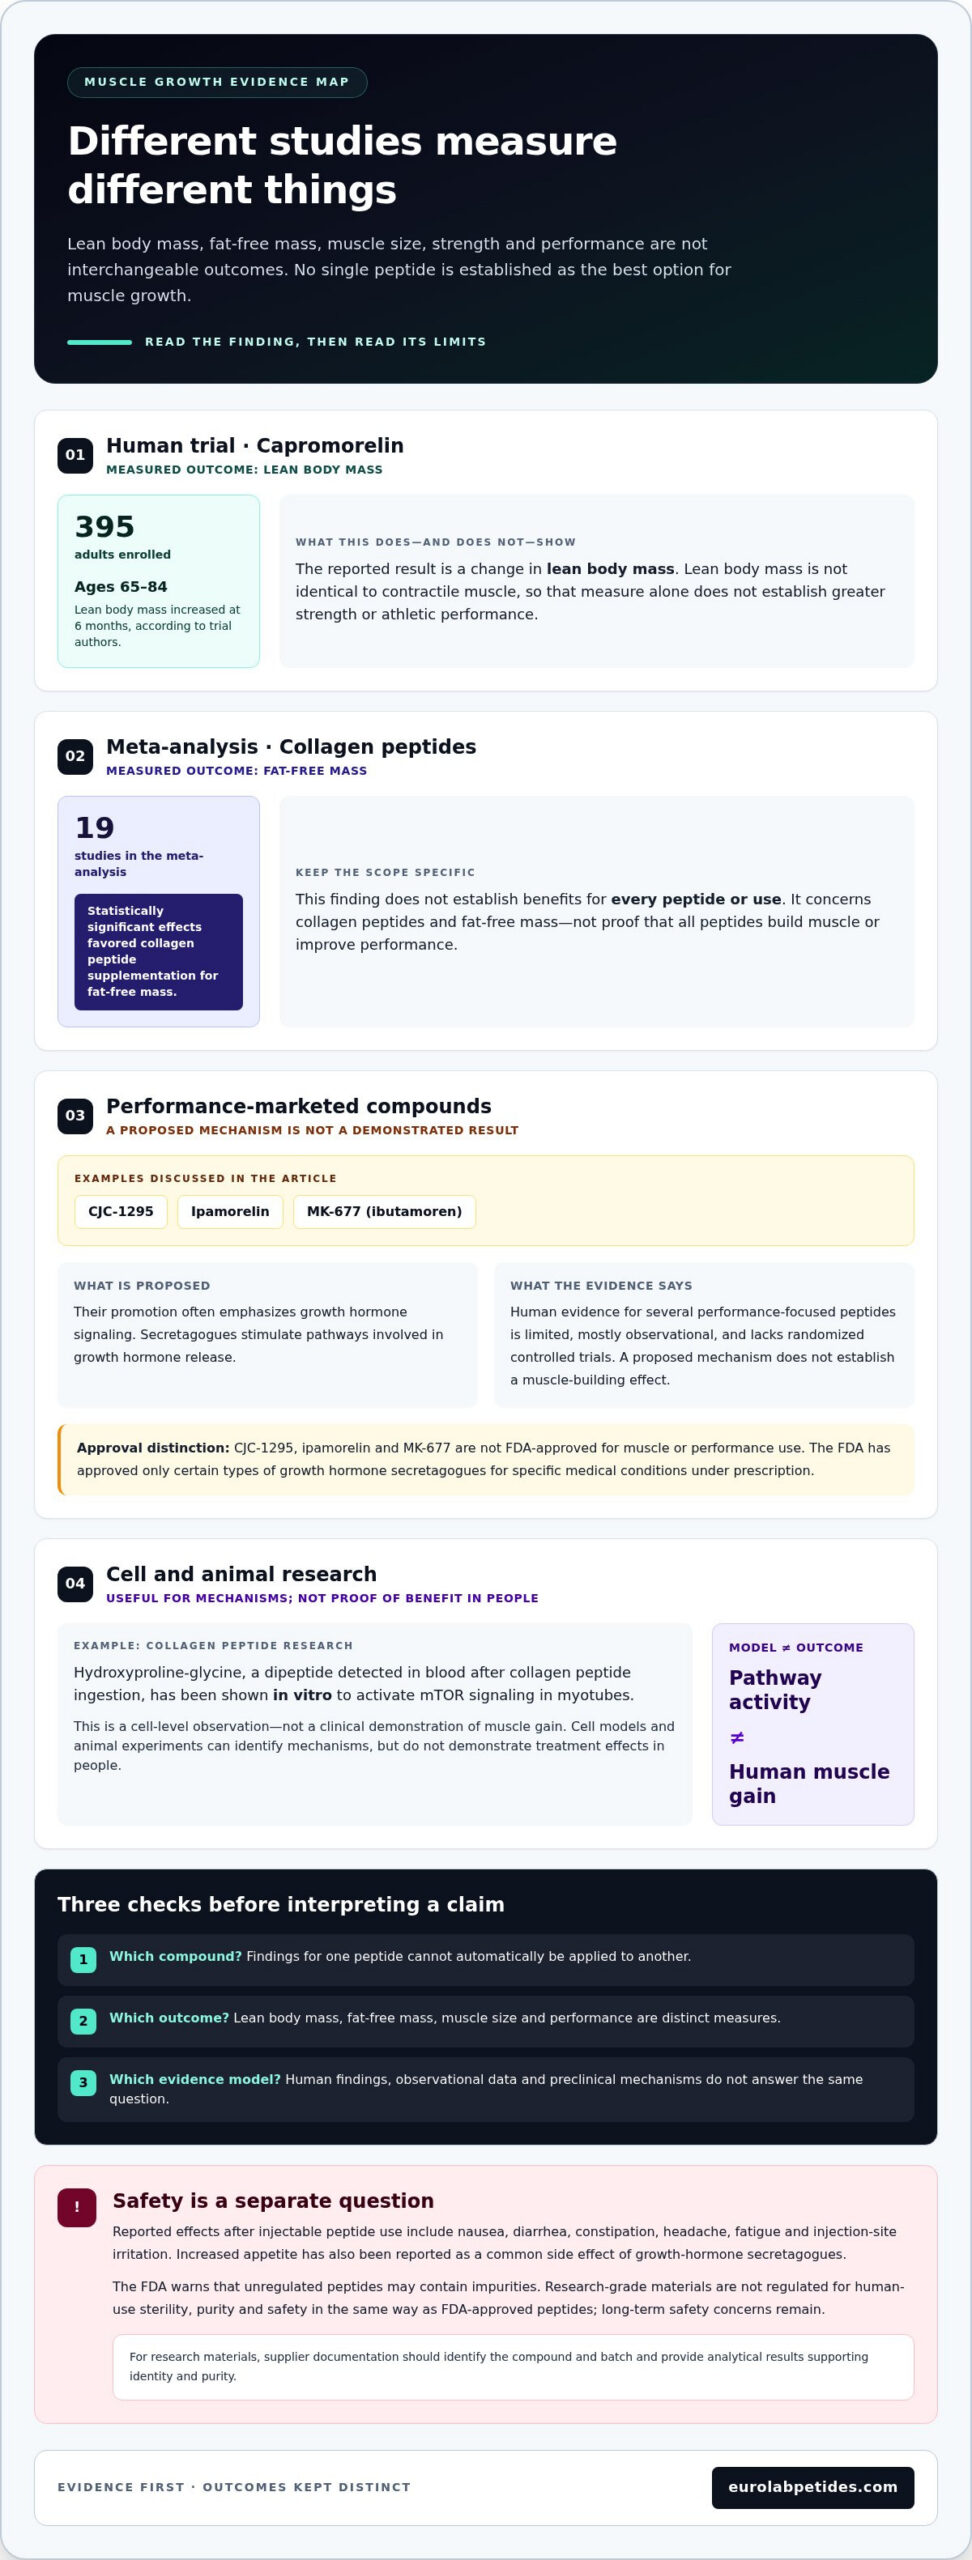
No single peptide is established as the best option for muscle growth. Human findings differ by compound and outcome, so lean body mass, muscle size, and performance must be assessed separately.
Peptides Marketed for Muscle Growth
Peptides marketed for muscle growth and athletic performance include growth-hormone secretagogues such as CJC-1295 and ipamorelin, and the oral compound MK-677, also called ibutamoren. Their promotion often emphasizes growth hormone signaling, but a proposed mechanism does not establish a muscle-building effect. For research, distinguish measured outcomes from wellness marketing claims and supplements discussed without controlled human evidence.
Growth Hormone Secretagogues and Muscle Performance
Growth-hormone secretagogues stimulate pathways involved in growth hormone release, making them a subject of muscle-performance research. The FDA has approved only certain types of growth hormone secretagogues for treating specific medical conditions under prescription; CJC-1295, ipamorelin, and MK-677 are not FDA-approved for muscle or performance use. A 2017 review identified increased appetite as a common side effect. That matters when interpreting body-composition effects, since appetite can influence energy intake.
Lean Body Mass and Muscle Growth
Lean body mass is not identical to contractile muscle, so a change in that measure alone cannot establish greater strength or athletic performance. A randomized capromorelin trial enrolled 395 adults aged 65-84. According to Capromorelin trial authors, capromorelin increased lean body mass at 6 months in adults aged 65-84. Separately, according to Meta-analysis authors, a meta-analysis of 19 studies found statistically significant effects favoring collagen peptide supplementation for fat-free mass. These findings concern different compounds and outcomes, so they shouldn’t be treated as interchangeable proof of muscle growth.
Evidence Across Human and Preclinical Research
Human evidence is limited: data on several performance-focused peptides are mostly observational and lack randomized controlled trials. Animal experiments and cell models can identify mechanisms, but they don’t demonstrate treatment effects in people. For popular compounds, compare human study design, measured outcomes, and known safety concerns; price alone cannot establish evidence quality or safety. Research-grade supplier documentation should identify the compound and batch and provide analytical results supporting identity and purity. In a laboratory, follow the material’s validated storage and reconstitution protocol, use aseptic handling where required, and record batch, solvent, and preparation details.
These comparisons support a cautious interpretation: growth hormone signaling, lean-mass changes, and muscle performance are related research questions, but they are not identical endpoints. Assess each compound by its human evidence, specific outcome, and adverse-effect profile rather than by marketing claims.
What are some side effects of peptides?
Reported effects after injectable peptide use include nausea, diarrhea, constipation, headache, fatigue, and injection-site irritation. Symptoms vary by compound and exposure. Safety interpretation also depends on whether a peptide is approved for a specific clinical treatment or marketed for muscle research without that approval.
Peptides, Proteins, and Signaling
Peptides are short chains of amino acids, the building blocks of proteins. Insulin, endorphins, and growth hormone-releasing hormone are examples produced by the body. A peptide can bind a receptor or influence a signaling pathway, prompting processes such as hormone release. That biological action doesn’t establish efficacy for muscle growth or prove safety in people.
Anabolic signaling describes pathways that regulate processes such as muscle protein synthesis. For example, the mTOR pathway helps coordinate cellular responses to nutrients and growth signals. A finding in a cell model can clarify how a peptide interacts with this pathway, but it cannot by itself show that the same effect occurs in human muscle or improves strength.
Collagen Peptides and Protein Synthesis
Collagen peptides differ from complete dietary proteins in amino-acid composition. Their spectrum is incomplete, and their leucine content is low, which may imply a small anabolic effect. A 12-week resistance-training trial combined exercise with collagen peptide supplementation. That study design helps examine responses alongside training, but collagen findings shouldn’t be generalized to every peptide or treated as proof of equal effects on muscle protein synthesis.
One proposed mechanism involves hydroxyproline-glycine, a dipeptide detected in blood after collagen peptide ingestion. In vitro, this dipeptide has been shown to activate mTOR signaling in myotubes. This is a cell-level observation, not a clinical demonstration of muscle gain. When interpreting efficacy, keep the model, measured pathway, and human outcome distinct.
Safety Interpretation
Unregulated injectable peptides can carry risks beyond reported symptoms. The FDA warns that unregulated peptides may contain impurities, while abnormal immune responses can include allergic reactions or autoimmune issues. Research-grade materials are not regulated for human-use sterility, purity, and safety in the same way as FDA-approved peptides. These distinctions matter when assessing laboratory materials separately from medicines used in clinical care.
Insulin illustrates why peptide identity alone doesn’t determine risk or use: it is a peptide medication used to treat health conditions. Its medical role differs from that of compounds marketed online for athletic performance. In research, document the compound, batch identity, analytical results, and handling conditions. These records help distinguish observed effects from errors in material identification or preparation.
For studies centered on tissue response, tissue repair and recovery research provides a relevant research area. Keep laboratory findings, clinical treatment, and human-use decisions separate. Each addresses a different question, and evidence from one context cannot automatically establish safety or efficacy in another.
Potential side effects and long-term safety
Safety depends on the compound, exposure, and context of use. Reported side effects of injectable peptides include nausea, diarrhea, constipation, headache, fatigue, and injection-site irritation. Unregulated products add concerns about contamination and abnormal immune responses, including allergic reactions or autoimmune issues.
Reported Effects and Immune Risks
Symptoms can involve digestion, energy, pain, or the injection site. These reports don’t establish a shared side-effect profile across every peptide. A 2017 review identified increased appetite as a common effect of growth hormone secretagogues. That signal is relevant when interpreting body-composition outcomes, since appetite may affect eating patterns alongside exercise.
Product quality also shapes risk. The FDA warns that unregulated peptides may contain impurities, and research-grade peptides are largely unregulated for human-use sterility, purity, and safety compared with FDA-approved peptides. Abnormal immune responses can include allergic reactions or autoimmune issues. A purity result alone doesn’t establish sterility or clinical safety, so these quality dimensions should not be treated as interchangeable.
MK-677 and Hormone Measurements
MK-677, also called ibutamoren, is an oral growth hormone secretagogue described as once-daily. Growth-hormone peptides can shift IGF-1 within 30 days, making IGF-1 a distinct measurement from testosterone. A change in one hormone shouldn’t be used to infer a change in another. Testosterone is a separate endocrine endpoint; interpretation requires a direct measurement rather than assumptions based on growth hormone signaling.
Oral administration doesn’t establish long-term safety. The relevant assessment includes the compound, exposure period, measured hormone markers, appetite effects, and reported symptoms. For MK-677, appetite is a specific effect to track alongside body-composition measures. These observations describe research considerations, not a dosing or treatment recommendation.
Long-Term Evidence and Practical Limits
There are no large, multicenter trials evaluating injectable peptides’ safety, dosage, or long-term use in athletes. This limits conclusions about cumulative exposure, delayed adverse effects, and safety during repeated exercise or injury recovery. Findings from short observations cannot resolve those longer-term questions.
Human use also differs from laboratory research. A research-grade peptide isn’t equivalent to a medicine approved for human treatment, and product labeling doesn’t establish suitability for injection. Harvard physician Pieter Cohen advises people not to inject themselves with peptides. Competitive athletes also need to consider that growth-hormone secretagogues and related GH-axis agents may be prohibited in sport. Laboratory testing can detect peptide fragments and metabolites, creating a risk of a positive test.
For safety interpretation, separate three questions: what symptoms occurred, what material was used, and how long it was observed. Record compound identity, batch, exposure context, and outcomes consistently. This structure helps distinguish a compound-related effect from contamination, an immune response, or another factor, while keeping laboratory evidence separate from clinical treatment decisions.
Peptide basics and how peptides act in the body
Peptides are chains of amino acids linked by peptide bonds. The human body produces thousands of peptide types, including insulin, endorphins, and growth hormone-releasing hormone. Their structures vary in length and sequence, affecting how they interact with cells. Proteins are also amino-acid chains, but generally form larger, more complex structures. These distinctions help explain why a peptide’s biological purpose depends on its specific composition.
Many peptides act as signaling molecules. A signal reaches a target cell, binds a compatible receptor, and influences activity inside that cell. Insulin, for example, signals through its receptor to regulate processes involving glucose. Growth hormone-releasing hormone acts on a different target, stimulating growth hormone release. These examples show why “peptide” describes a broad molecular class, not one shared effect.
In muscle research, trace the steps of a proposed action to interpret it. First, identify the peptide and its sequence. Next, determine which receptor or pathway it engages. Then assess the measured response, such as a change in cellular signaling or gene expression. A response in a muscle-cell model describes that model; it doesn’t automatically establish an effect across whole-body physiology.
Peptides and anabolic steroids are chemically distinct. Peptides are amino-acid chains, while anabolic steroids are typically synthetic versions of naturally occurring male hormones such as testosterone. Their molecular structures and biological targets differ. This matters in sports research because similar marketing claims, such as enhanced performance, don’t make the compound classes equivalent. Mechanism, target tissue, and measured outcome must be evaluated separately.
Nutrition also affects how researchers interpret muscle-related signals. Dietary protein supplies amino acids used in protein synthesis, while peptide signaling can influence cellular activity through different mechanisms. These roles are related but not interchangeable. For example, a signal that stimulates a pathway in a cell model doesn’t show that a supplement improves muscle composition in people. The experimental context shapes what a result can support.
For peptides for muscle tissue research, define the purpose before selecting an endpoint. A study may examine receptor binding, hormone release, inflammation, or muscle-cell responses; each asks a different question. Separate biochemical activity from tissue-level effects, then distinguish those findings from outcomes measured in people. This framework keeps claims about how a peptide may enhance a response tied to the specific compound, model, and result evaluated.
Inflammation and muscle recovery
Inflammation is part of the tissue response to exercise and injury, but reducing an inflammatory signal doesn’t automatically restore muscle function. In peptide research, recovery can refer to different outcomes: wound closure, tissue structure, pain, or strength. These endpoints aren’t interchangeable. A compound that affects one pathway in an animal model hasn’t thereby demonstrated improved recovery in patients.
BPC-157 illustrates the gap between proposed mechanisms and human evidence. Test-tube and animal studies suggest possible effects on injury recovery and wound healing, but evidence of benefits in people is largely absent. The human evidence includes a single case series involving knee pain, with methodological flaws and no control group. That report cannot determine whether BPC-157 caused the observed outcome.
CJC-1295 and GHK-Cu also appear in preclinical work on injury recovery or wound healing. Findings from cells and animals can help identify biological pathways for further study. They don’t establish that either peptide repairs injured human muscle, reduces inflammation safely, or restores strength. The model matters: a wound-healing result, for example, is not equivalent to a muscle-recovery result after exercise.
Joint tissue adds another complication. Athletes have an increased risk of articular cartilage lesions that can lead to functional joint pain. Stimulating collagen synthesis with biologically active peptides is one therapeutic approach to treating or preventing degenerative articular processes. That rationale concerns cartilage and collagen biology; it shouldn’t be presented as proof of muscle regeneration or a treatment outcome for every injury.
For a useful evidence appraisal, break the question into three steps. Identify the tissue studied, such as muscle, a wound, or articular cartilage. Then identify the model, such as a cell culture, animal, or human case series. Finally, check the measured endpoint: inflammation markers, tissue repair, pain, or physical strength. A favorable finding at one step doesn’t answer the other questions.
The central takeaway is that preclinical promise remains distinct from demonstrated human recovery. BPC-157 lacks human clinical evidence for muscle healing and recovery, while evidence for CJC-1295 and GHK-Cu benefits in people is largely absent. Long-term effects and practical relevance for injured patients remain unknown. Researchers examining recovery should therefore define the tissue and outcome precisely, rather than treating “healing” as a single measurable result.
EuroLab Peptides: Longevity & Vitality Research
EuroLab Peptides supports scientific inquiry through its Longevity & Vitality Research offering, alongside Tissue Repair & Recovery Research for studies examining tissue response. These research areas are relevant when your work moves from evaluating evidence to investigating peptide-related biological questions in a laboratory setting. EuroLab Peptides uses in-house and independent third-party laboratory testing as part of its quality-control process, with purity and consistency as key considerations for research materials.
Choose the research area that aligns with your study’s focus, whether that is tissue repair, recovery, or longevity. For research-grade materials, keep laboratory use distinct from human consumption, medical advice, and treatment. Visit EuroLab Peptides to explore its research offerings.
Define the Next Research Question
Progress in muscle research depends on turning broad claims into testable questions. For peptides for muscle tissue research, define the biological target, model, and outcome before interpreting a result. This framework can help focus future investigations and make comparisons across studies more meaningful.
EuroLab Peptides offers research areas including Longevity & Vitality Research, Weight Management Research, and Tissue Repair & Recovery Research. These areas provide a relevant starting point when your scientific inquiry extends beyond muscle response to related tissue or metabolic questions. Select the focus that best matches your research objective, then proceed with a clearly scoped research plan.
For information on research offerings, contact EuroLab Peptides. A precise question is a strong foundation for the next stage of investigation.
Frequently Asked Questions
What are peptides and how do they work?
Peptides are molecules whose amino-acid sequences influence how they interact with biological targets. In the body, a signal such as insulin binding to its receptor can alter cellular activity. In research, the key questions are what the specific molecule targets and what response is measured. A receptor interaction, a change in gene expression, and a whole-body effect represent different levels of evidence.
Are peptides safe?
Safety depends on the specific compound, its quality, and how it’s used. Reported effects include digestive symptoms, headache, fatigue, and injection-site irritation; unregulated injectable products can also contain impurities or trigger abnormal immune responses. Research-grade materials are intended for laboratory research, not human consumption or clinical use. For experimental interpretation, record the material’s identity and batch separately from observed symptoms and outcomes.
Do peptides affect testosterone?
A growth-hormone signal and a testosterone measurement represent different endocrine endpoints. A change in growth hormone or IGF-1 doesn’t, by itself, establish a testosterone change. In a study examining testosterone, treat it as a separate outcome and interpret it alongside the compound, measured markers, and study design. Don’t infer an effect on testosterone solely from a peptide’s proposed action on another hormone pathway.
How are peptides taken?
Administration depends on the compound and context. MK-677, also called ibutamoren, is described as an oral secretagogue; other peptides marketed online are injectable. These routes don’t make research materials suitable for human use. In laboratory work, follow the compound-specific research protocol and document preparation and handling. Avoid treating a research protocol as personal dosing guidance or as instructions for clinical treatment.
How do they work for bodybuilding?
Bodybuilding claims generally focus on whether a compound could influence muscle size, lean mass, or recovery alongside resistance exercise. Measure these outcomes separately: increased lean mass doesn’t automatically mean greater strength or improved performance. Some reports combine peptides with training, making it difficult to attribute an observed change to the compound alone. Training, nutrition, and sleep also shape muscle adaptation and should be considered when interpreting results.
How does the CJC-1295 and ipamorelin stack work?
The combination is discussed as pairing two growth-hormone secretagogues, with the aim of influencing growth-hormone signaling. It’s typically described as being taken before bed, but that description isn’t a recommendation. CJC-1295 and ipamorelin aren’t FDA-approved for muscle or performance use. A proposed mechanism doesn’t establish improved bodybuilding outcomes, and the combination shouldn’t be treated as a proven treatment.
What are the health benefits of peptides?
Some peptide medicines have specific medical uses, which differ from muscle-building claims. Insulin and GLP-1 medicines, including semaglutide and tirzepatide, are used to treat conditions such as diabetes and obesity. Tesamorelin is FDA-approved to reduce excess abdominal fat in adults with HIV who have lipodystrophy. Those examples don’t establish that other peptides provide the same benefits or are appropriate for muscle research.
What peptides are commonly studied in muscle tissue research?
Examples include collagen peptides, growth-hormone secretagogues such as CJC-1295 and ipamorelin, MK-677, and BPC-157. They represent different research questions, from collagen-related responses to growth-hormone signaling or injury models. For peptides for muscle tissue research, identify the compound and model before comparing findings. A result involving muscle cells or animals shouldn’t be presented as evidence of a human bodybuilding effect.
